Executive Summary
Group Purchasing Organizations occupy a central and largely unquestioned position in the healthcare procurement ecosystem. Nearly every hospital in the United States participates in at least one GPO, and the strategy seems straightforward: aggregate purchasing volume, negotiate from scale, reduce sourcing overhead and secure pricing that standalone institutions cannot achieve on their own.
That value proposition seems obvious; GPOs provide contract access, pricing benchmarks, administrative efficiency and scale leverage that many organizations would struggle to replicate independently. The question is not whether they add value – the question is whether their economic structure is fully aligned with the financial objectives of the hospitals they serve.
It is not.
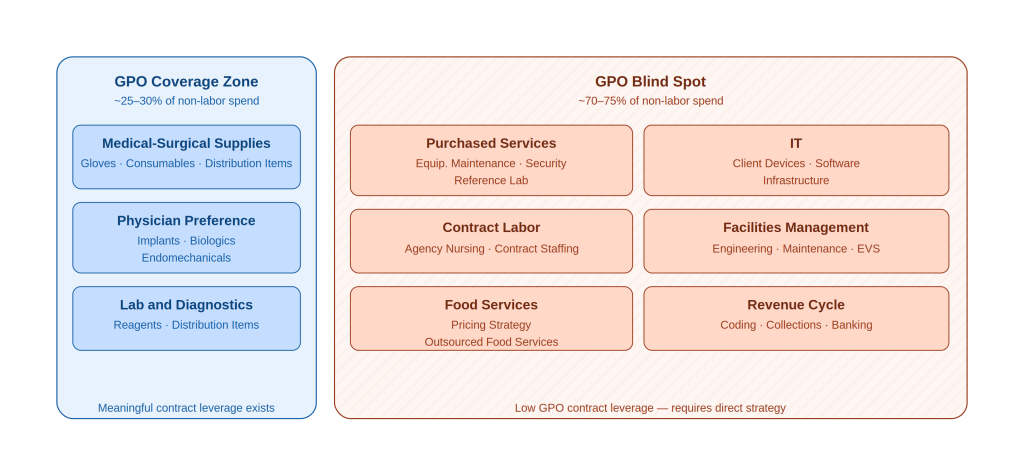
GPOs are funded primarily through administrative fees paid by vendors as a percentage of purchase volume, an arrangement permitted under federal safe harbor regulations. A GPO whose revenue scales directly with total spend cannot be perfectly aligned with aggressive enterprise-wide cost reduction objectives. Compliance frameworks limit the pursuit of lower-cost alternatives, local negotiating gains are often offset in part by GPO fee structures, and some of the most powerful cost levers, utilization management, standardization, make vs. buy, revenue enhancement and strategic partnerships fall largely outside GPO influence.
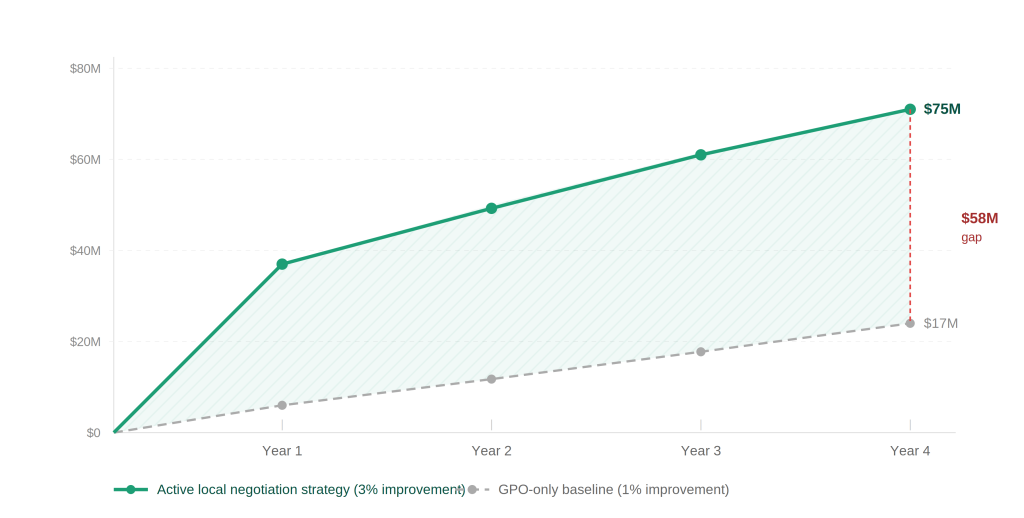
For a health system carrying $1 billion in annual non-labor spend, a one percent improvement in total economics represents $10 million in margin impact. At three percent, that figure rises to $30 million. For organizations operating on thin margins, those are not rounding errors, they are the difference between financial stability and uncertainty.
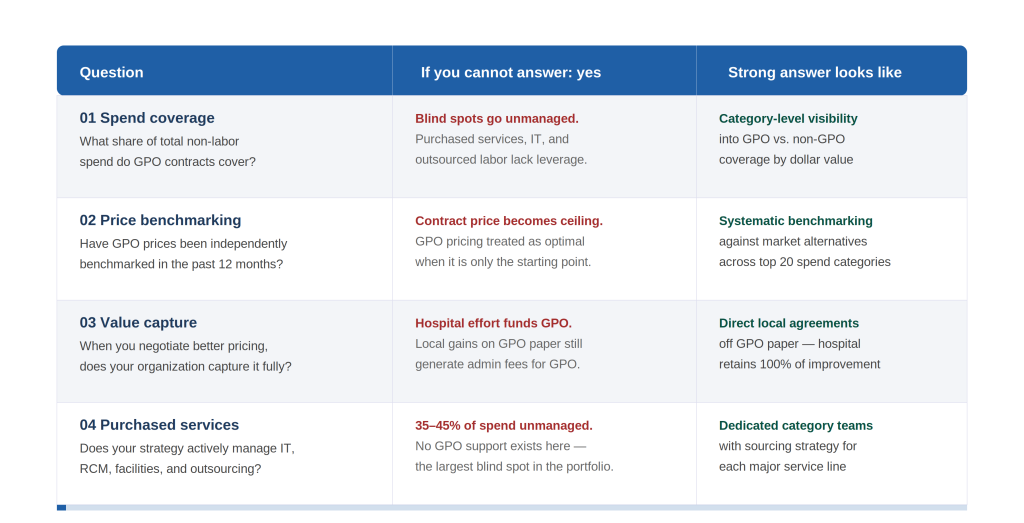
This paper examines where GPO incentives diverge from hospital interests, quantifies the financial stakes for executive leadership, and offers a framework for using GPO relationships strategically in a broader cost management strategy rather than relying on them to drive financial improvement goals.
The Historical Evolution of Group Purchasing Organizations
Group Purchasing Organizations began in the early twentieth century as cooperative buying arrangements among hospitals operating in fragmented markets. Individual institutions lacked scale and procurement sophistication, suppliers often dictated pricing, and administrative resources were limited. By pooling demand, hospitals gained leverage, reduced overhead, and secured better terms.
The modern GPO industry took shape in the 1980s when two forces converged. Reimbursement pressure intensified following Medicare’s shift to prospective payment systems, putting cost reduction at the top of every hospital CFO’s agenda. Simultaneously, Congress formalized the legal safe harbor permitting vendors to pay administrative fees to GPOs, a regulatory change that institutionalized a vendor-funded revenue model tied directly to purchasing volume and altered the economic foundation of the industry permanently.
Administrative fees provided scalable, predictable revenue that fueled consolidation. By the early 2000s, a small number of national organizations – Vizient, Premier, and HealthTrust Performance Group had emerged as dominant players overseeing hundreds of billions in annual purchasing volume. As health systems consolidated, GPOs expanded beyond basic contracting into physician preference items, capital equipment, analytics, purchased services, and advisory functions.
Today a hospital may simultaneously participate in a national GPO, a regional alliance, and an aggregator overlay, with pricing tiers and rebates dependent on compliance metrics across multiple portfolios. What began as cooperative purchasing has evolved into a complex, vendor-funded structure whose economics are not always transparent to the members it serves.
Where Misalignment Becomes Visible
Commodity and Medical-Surgical Categories
In commodity medical-surgical supplies, GPO pricing is structured around compliance. Diverting volume to a lower-cost alternative can jeopardize portfolio discounts across an entire category. The result is a structure in which hospitals are financially penalized for pursuing better economics outside the contract, not because the alternative is inferior, but because compliance thresholds protect fee revenue.
Physician Preference Items
National contracts in physician preference categories typically establish maximum pricing frameworks. Many organizations incorrectly treat these ceilings as the best available price. Local negotiations, particularly those supported by data and tailor-made strategies, frequently achieve significantly better terms. The gap between GPO contract pricing and locally achievable pricing in implants, cardiovascular devices, and other high-value categories can be significant and lead to multi-million-dollar savings potential.
Local Negotiations and Fee Capture
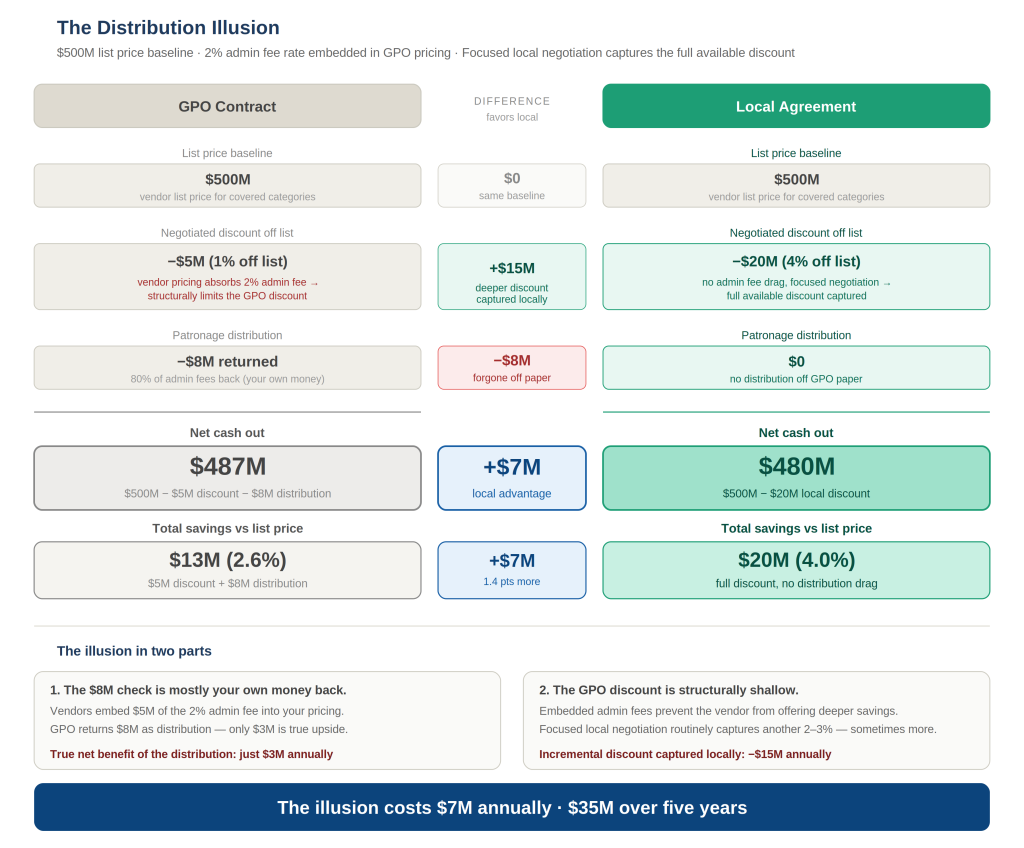
When hospitals do negotiate improved pricing independently, GPOs often prefer that those agreements remain on their contract paper, preserving administrative fee flows and compliance metrics. If pricing improvements originate from hospital-led effort but remain on GPO paper, administrative fees may still apply. The hospital captures some, but not all, of the value. The economics of the improvement are shared with the GPO even when the GPO contributed nothing towards achieving it.